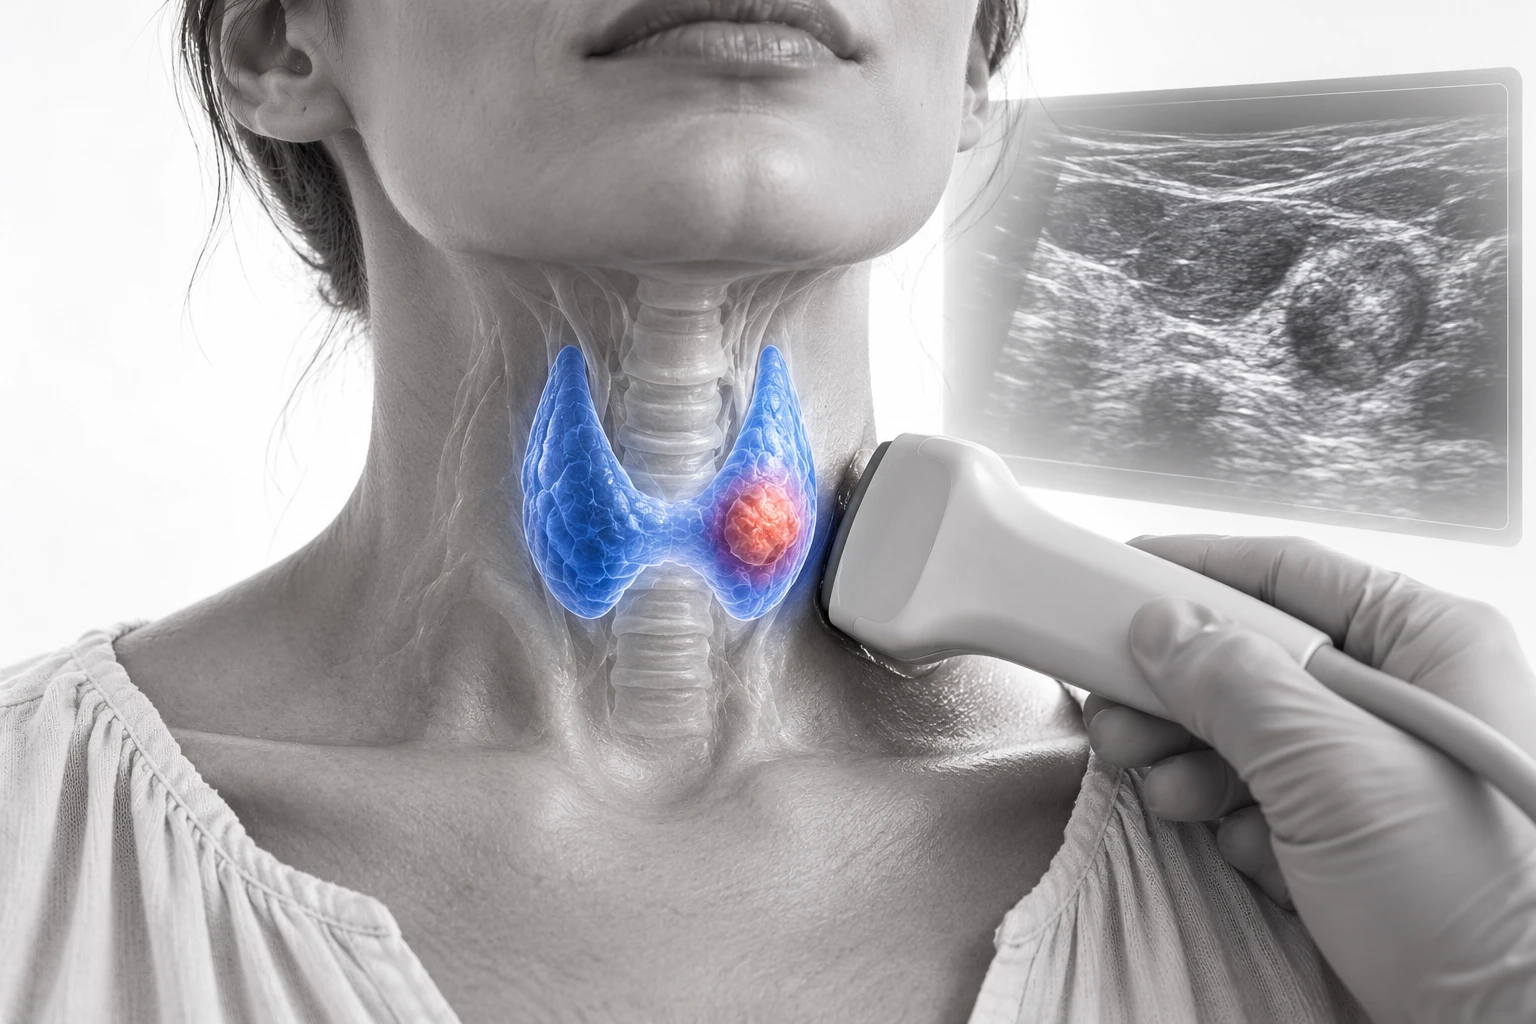
توضیح تکمیلی: سرطان تیروئید چیست؟
Understanding thyroid cancer
- سرطان تیروئید از سلولهای این غده در جلوی گردن شروع میشود.
- انواع پاپیلری، فولیکولار، مدولاری و آناپلاستیک رفتارهای متفاوتی دارند؛ بیشتر ندولهای تیروئید سرطانی نیستند.
- Thyroid cancer begins in the gland at the front of the neck.
- Papillary, follicular, medullary and anaplastic cancers behave differently; most thyroid nodules are not cancer.
توضیح تکمیلی: جایگاه و اهمیت
Why it matters
- بیشتر انواع تمایزیافته روند آهستهتر و پیشآگهی مناسبی دارند؛ اما همه زیرنوعها یکسان نیستند.
- انتخاب بررسی و درمان متناسب، از درمان غیرضروری هم جلوگیری میکند.
- موارد جدید در ۲۰۲۴: ایران ۶٬۵۳۸؛ جهان ۹۵۹٬۲۸۱.
- Many differentiated thyroid cancers grow slowly and have favorable outcomes, but subtypes differ.
- Appropriate assessment also helps avoid unnecessary treatment.
- New cases in 2024: Iran 6,538; worldwide 959,281.
توضیح تکمیلی: علائم و نشانهها
Signs and symptoms
- توده تازه گردن یا رشد سریع توده
- گرفتگی صدای ماندگار یا مشکل بلع
- ندول ممکن است بدون درد و آزمایش هورمون تیروئید طبیعی باشد.
- New neck lump or rapid growth of a lump
- Persistent hoarseness or swallowing difficulty
- A nodule may be painless with normal thyroid hormone tests.
توضیح تکمیلی: عوامل خطر و علتها
Risk factors and causes
- پرتوتابی گردن در کودکی
- زمینه خانوادگی و تغییرات ارثی، بهویژه در نوع مدولاری
- نیاز به نمونهبرداری با اندازه و ظاهر سونوگرافی ندول تعیین میشود.
- Childhood neck irradiation
- Family history and inherited variants, especially in medullary cancer
- Nodule size and ultrasound appearance guide biopsy decisions.
توضیح تکمیلی: روشهای تشخیص
Diagnostic assessment
- سونوگرافی تیروئید و گردن پایه ارزیابی است و بر اساس الگو و اندازه FNA (نمونهگیری با سوزن باریک؛ سلولها را برای بررسی آزمایشگاهی جمع میکند) انجام میشود.
- TSH (هورمون محرک تیروئید؛ آزمایش آن کارکرد تیروئید را نشان میدهد) و در موارد منتخب تستهای مولکولی کمککنندهاند.
- در medullary cancer، calcitonin و ارزیابی ژنتیک RET (ژنی که بعضی تغییرهای ارثی یا اکتسابی آن در سرطان تیروئید اهمیت دارد) اهمیت دارند.
- Thyroid and neck ultrasound are central, with FNA (fine-needle aspiration, which collects cells for laboratory examination) based on sonographic pattern and size.
- TSH (thyroid-stimulating hormone, a blood test of thyroid function) and selected molecular testing (a test that looks for gene or molecular changes; results must be interpreted with the disease type) can help.
- In medullary cancer, calcitonin and RET (a gene whose inherited or acquired changes matter in some thyroid cancers) genetic evaluation are important.
توضیح تکمیلی: مرحلهبندی سرطان
Cancer staging
- TNM (روش توصیف اندازه و گسترش تومور، درگیری غدد لنفاوی و پخششدن به بخشهای دور بدن) استفاده میشود و در سرطانهای papillary و follicular سن نیز در مرحله بیماری نقش دارد.
- علاوه بر مرحله بیماری، risk stratification پس از جراحی برای پیشبینی عود و تصمیم درباره ید رادیواکتیو اهمیت دارد.
- TNM (a system describing tumor size and local spread, lymph-node involvement and distant spread) is used, and age also affects staging for papillary and follicular cancers.
- Beyond stage, postoperative recurrence-risk stratification helps guide radioactive iodine and follow-up.
توضیح تکمیلی: درمان
Treatment
- گزینهها شامل لوبکتومی یا تیروئیدکتومی کامل، در موارد منتخب ید رادیواکتیو و درمان هورمون تیروئید هستند.
- بیماری پیشرفته میتواند به درمانهای هدفمند بر اساس تغییرات مولکولی نیاز داشته باشد و anaplastic cancer نیاز به تصمیم سریع چندتخصصی دارد.
- Options include lobectomy or total thyroidectomy, radioactive iodine in selected cases and thyroid-hormone therapy.
- Advanced disease may need molecularly targeted treatment, while anaplastic cancer requires rapid multidisciplinary care.
پیگیری و پیشآگهی
Prognosis and follow-up
- بیشتر سرطانهای تمایزیافته تیروئید پیشآگهی بسیار خوبی دارند.
- پیگیری بر معاینه، thyroglobulin در موارد مناسب و سونوگرافی گردن است و بر اساس خطر عود تنظیم میشود.
- Most differentiated thyroid cancers have an excellent prognosis.
- Follow-up uses examination, thyroglobulin when appropriate and neck ultrasound, tailored to recurrence risk.
کارهای مهم برای بیمار
Practical next steps
- نوع دقیق پاتولوژی، extent جراحی، احتمال نیاز به ید رادیواکتیو و هدف TSH را روشن کنید.
- در medullary cancer یا سابقه خانوادگی درباره تست ژنتیک سؤال کنید.
- Clarify histology, required extent of surgery, whether radioactive iodine is likely and the TSH target.
- In medullary cancer or a family history, ask about genetic testing.